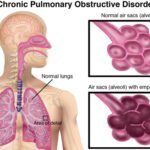
To understand your COPD stage, ask the clinician which grading system was used and how the actual assessment supports it. NHLBI describes diagnosis using symptoms, history and testing, with spirometry as the main test. A symptom list or a home oxygen reading does not replace that process.
Start with the spirometry explanation
Spirometry measures how much air you breathe out and how quickly. NHLBI explains that the team may compare measurements before and after an inhaled medicine, and that results help assess seriousness and treatment goals.
Ask for the report in language you understand. What does each term mean? If a number is a percentage, what is it being compared with? Does the clinician mean an airflow grade, symptoms, flare-up risk or a broader description of your needs when saying stage?
These are clarification questions, not cutoffs for grading yourself. This article does not reproduce a numerical staging chart because the inspected patient guidance is not a complete current grading manual. Ask the team to identify the system it is actually applying.
Do not make every measurement mean stage
People with COPD do not all have the same symptoms. Describe what is difficult in daily life and whether it is new. A symptom account adds information but does not independently assign a grade.
NHLBI says a chest X-ray cannot diagnose COPD, although it can help investigate other conditions. Different tests have different roles. Ask what each result is intended to answer instead of treating a chest picture, walking distance and airflow measurement as interchangeable scores.
Ask what the label changes
NHLBI describes treatment selected for symptoms and seriousness. Ask what the assessment means for your current plan, what will be reviewed and which practical help is relevant. A stage label should lead to an explained care discussion, not become a personal life-expectancy calculation.
Sudden worsening needs prompt contact even if you were previously told the condition was mild. An old label cannot establish that a new episode is safe to ignore. Keep the routine review and urgent-response instructions distinct.
Sources and scope
The linked patient education explains testing and care, not a full staging algorithm or an interpretation of your report. Not yet medically reviewed.